When is a carb not a carb? The great fructose experiment.
All material on this website is provided for your information only and may not be construed as medical advice or instruction. No action or inaction should be taken based solely on the contents of this information; instead, readers should consult appropriate health professionals on any matter relating to their health and well-being.
By 2019, you’ve probably heard someone claim at one point that “sugar is bad.” Many people don’t even know what “sugar” is, so this blog post is going to attempt to teach some “sugar science.” First, I’ll do some basic chemistry regarding sugar, and finally, I’ll take you to my own personal experiment that is relevant to people with type 1 diabetes. If you think you already know the sugar science and just want to skip to the experiment, click here.
What is Sugar?
First, we must define sugar. If you’re like most people, you imagine “table sugar” when you hear the word. In fact, many think that table sugar is the only sugar. It turns out, that table sugar is actually a combination of two other sugars in a 50/50 ratio: glucose + fructose.

What is sugar? When most people think of sugar, they imagine “table sugar” which is made of sucrose molecules.
Now that you think about it, you’ve probably already heard of glucose, fructose, and sucrose. In fact, you’ve probably already heard of lactose too. Notice anything in common between these words? They all end in “-ose“. In chemistry, the “-ose” ending means a molecule is a sugar. This rule works really well with chemistry, but not so well with other words that end in “-ose” such as “nose” or “panty hose“. Neither one of those will give you a sweet taste in your mouth.
In natural foods, you’ll most commonly encounter the following sugars:
- Glucose (GL)
- Fructose (FR)
- Galactose (GA)
Those 3 sugars (called “monosaccharides”) make up the backbones of two other sugars you have probably already heard of as well:
- Sucrose (GL + FR)
- Lactose (GA + GL)
Notice how in the 2nd list that Sucrose is a combination of GL + FR. That means that a Sucrose molecule (table sugar) actually consists of one Glucose and one Fructose bound together. When two monosaccharides are bound together, they become a disaccharide. And those monosaccharides can combine into much longer molecules, such as amylose, which looks something like this: (GL + GL + GL + GL + GL + GL + GL……….).
Because amylose consists of hundreds or thousands of glucose molecules joined together, it is called a polysaccharide. Now, to review:
- Saccharide means “sugar”
- Mono means “one”
- Di means “two”
- Oligo means “few” (a short chain)
- Poly means “many” (a long chain)
Notice the pattern here… amylose ends in “-ose“, and it consists entirely of glucose molecules. Amylose is one of the two major components of starch. The other is called amylopectin, which is also made entirely of glucose, but has a branched structure rather than the mostly straight chains found in amylose.
In food, we tend to call the monosaccharides and disaccharides “sugar.” Most of these molecules taste sweet (to varying degrees). But here’s something interesting: amylose is a long chain of glucose molecules, yet it doesn’t taste sweet at all!
How do I know? Because a regular potato isn’t particularly sweet, even though it contains lots of starch! About 20-30% of the starch in a typical potato is amylose, with most of the remainder being amylopectin. That’s 20-30% of the starch, not 20-30% of the entire potato.
So a potato contains a lot of glucose molecules joined together in long chains, but your taste buds don’t perceive those chains the same way they perceive individual sugar molecules. Just because you can’t taste the glucose doesn’t mean it isn’t there!
Other examples of starch-rich foods are bread, pasta, and rice. These foods don’t necessarily taste sweet, but much of their carbohydrate consists of glucose molecules joined together.
Once you eat these foods, digestive enzymes break down the starch into smaller molecules, eventually producing glucose that can be absorbed into your bloodstream. Both amylose AND amylopectin can be digested by human enzymes, including pancreatic amylase and enzymes in the small intestine.1
But here’s an interesting complication: Not all starch is digested at the same rate!
Cooking generally makes starch easier to digest because heat and water disrupt its crystalline structure, making it more accessible to digestive enzymes. This process is called “gelatinization.” When cooked starch cools, some of its molecules can reorganize into structures that resist digestion. This is called “retrogradation.”2
Starch that escapes digestion in the small intestine is called “resistant starch.” Some of it can be fermented by bacteria in the colon, producing short-chain fatty acids such as acetate, propionate, and butyrate.3
The important point is that a food like white bread can send your blood sugar skyrocketing even though it doesn’t taste particularly sweet! Depending on the food’s structure and preparation, the glucose response can be surprisingly rapid. However, the speed and extent of digestion vary, so we cannot assume that all starch behaves exactly like pure glucose.
So, what do we call all these different carbohydrates?
On an American Nutrition Label, we lump the sweet-tasting sugars, starches, and fiber together under one term: Total Carbohydrate.
Under Total Carbohydrate, you’ll typically see separate entries for Dietary Fiber and Total Sugars. What’s left over is often primarily starch, although it can also include other carbohydrates such as oligosaccharides and sugar alcohols.
Fiber is particularly interesting because human digestive enzymes generally cannot break it down into absorbable sugars. However, some fiber can be fermented by intestinal bacteria, producing short-chain fatty acids that the body can absorb and use for energy. This means fiber isn’t necessarily metabolically inert.
For insulin dosing, many people subtract some or all of the fiber from total carbohydrate. But the actual metabolic effect depends on the type of fiber, food composition, and individual physiology. In other words, simply subtracting fiber isn’t always a perfect calculation.
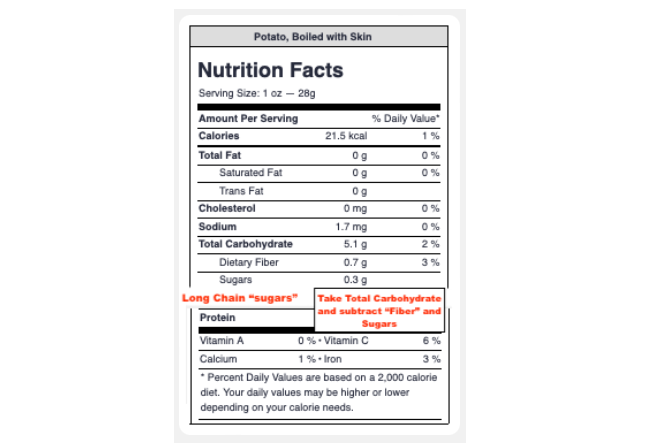
American Nutrition Labels group carbohydrates into Total Carbohydrate, with separate entries for Dietary Fiber and Total Sugars. The difference is often primarily starch, although other carbohydrates may also contribute. In this example, subtracting 0.7g of fiber and 0.3g of sugar from 5.1g of total carbohydrate leaves approximately 4.1g of other carbohydrates. The label alone doesn’t tell us exactly what those carbohydrates are or how quickly they’ll be digested.
Now that you know more about the different types of sugar, let’s learn a little more about what we are actually measuring when we “check our sugars” with a meter…
What are we measuring when we “check our sugars?”
If you have diabetes (or even if you don’t), you’ve probably heard people talk about “checking their sugars.” But what are we actually measuring? A glucometer measures the concentration of glucose in your blood, not fructose or galactose.
This distinction is important! For example, much of the starch in bread, potatoes, and pasta consists of long chains of glucose molecules (remember the GL + GL + GL + GL + GL……. molecules mentioned above?). Digestive enzymes break down these chains, releasing glucose that can be absorbed into your bloodstream.
Other sugars have different metabolic pathways. Galactose is largely metabolized by the liver, while fructose can be converted into glucose, lactate, glycogen, and other substances.
The important distinction: your glucometer measures the concentration of glucose in your blood at a particular moment. It doesn’t tell you how much glucose your body has produced, absorbed, or burned. Blood glucose reflects the balance between glucose entering and leaving the bloodstream.
But you may have noticed that I didn’t mention a couple of the simple sugars from the first list…. I didn’t mention “sucrose” (which is table sugar), nor did I mention “fructose”…
What about Fructose?
It turns out that unlike glucose based carbohydrates, fructose can experience a number of fates in the human body. When it comes to fructose, it’s kind of like a choose your own adventure. Here are some of the possible fates:4
- Fructose can be poorly absorbed by the intestines, so the body never “sees” it…
- Fructose can be “burned” to make ATP/CO2 (in liver, intestine, kidney, fat, and muscle)5
- Fructose can be converted to fat, glycerol, and glycogen.
- Fructose can be converted to glucose (but a glucometer cannot tell you how much conversion occurred)
It’s important to remember that table sugar (sucrose) is composed of equal numbers of glucose and fructose molecules. So when you eat a spoonful of table sugar, you’re consuming approximately equal amounts of glucose and fructose by weight.
But here’s where things get interesting! Your glucometer only measures glucose, and fructose follows different metabolic pathways. Fructose generally produces a much smaller immediate blood glucose response than an equivalent amount of glucose. However, some fructose can eventually be converted into glucose, so a small response on the meter doesn’t necessarily mean that the fructose has no effect on glucose metabolism or insulin requirements.
At the bottom of this post, I’ll discuss why this distinction could be important for people with diabetes.
The Experiment
The experiment is this: I will consume 14g (or 0.5oz) of pure fructose which I purchased from the health food store. Based on my own previous responses, I would normally expect to need about 2U of additional insulin for this much glucose, or else see a rise of more than 70mg/dL. This is my estimate, not a glucose control experiment performed alongside the fructose test.

Here is the fructose. I will consume 14g (0.5oz) of powdered fructose. I will not inject any additional insulin for this experiment; my usual basal insulin will still be active. If my blood glucose rises, one possible explanation is that some fructose was converted to glucose, although the meter alone cannot prove the pathway. Note that if I ate the same amount of glucose, it would raise my blood sugar by 70 points – which would be very clearly seen on the glucometer. Also, to compensate for this much glucose I would ordinarily need to inject 2U of insulin.
Although I cannot perform my own isotopic tracer experiment to see what happens to fructose when I eat it, I do have an interesting experimental situation because I have type 1 diabetes. I know exactly how much insulin I’ve injected, although I can’t know exactly how much is circulating in my blood or acting in my tissues at any particular moment. Unlike someone with normal insulin secretion, I don’t automatically produce a substantial additional insulin response when I consume a carbohydrate. For this experiment, I deliberately avoided injecting any additional insulin while continuing to have my normal basal insulin working in the background.

This is what the mass-equivalent dose of glucose tabs looks like. If you have diabetes, you probably recognize that this much glucose could produce a substantial glucose rise without additional insulin. Let’s see what happens when I consume this much fructose instead…
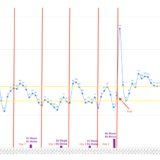
So, here is what the results of eating purified fructose with no extra insulin on board look like:

The experiment began at 10:14am and lasted roughly 1 hour, until 11:16am. Before beginning the experiment, I was fasted all night, and had stable blood sugars ~80 for the 3 hours leading up to the experiment. During the experiment, I just sat at my desk and performed no exercise (which could theoretically burn some glucose making it “disappear”). I expected an equivalent dose of glucose tablets to produce much higher readings, although I did not test glucose on the same day.
As you can see from the results above, eating pure fructose did NOT make my blood glucose meter budge. Yes, I got a reading of 87, but keep in mind that this is within the accuracy range of this meter; even if it is a real increase, it is small compared with the rise I would normally expect from an equivalent amount of glucose. So, what happened here?
What happened to the fructose?
The unfortunate answer is: I don’t know! But I DID learn something interesting.
My experiment showed that consuming 14g of pure fructose, without injecting any additional insulin, produced almost no detectable change in my blood glucose during the following hour.
But what actually happened to the fructose?
Maybe some wasn’t absorbed and was fermented by bacteria in my gut. Maybe some was burned for energy, stored as glycogen, converted into fat, or converted into glucose.
Here’s something important that I originally overlooked: Just because my blood glucose didn’t rise doesn’t mean that none of the fructose was converted into glucose!
Blood glucose concentration reflects the balance between glucose entering and leaving the bloodstream. Even though I didn’t inject any additional insulin, I still had my basal insulin working in the background. It’s entirely possible that some fructose was converted into glucose while glucose was simultaneously being removed from my bloodstream.
In fact, human isotope-tracer studies have found that an average of approximately 41% of ingested fructose was converted into glucose over a period of 3-6 hours in the studied conditions. These results, primarily from subjects without type 1 diabetes, cannot tell us exactly what happened to my 14g dose, but they demonstrate why my one-hour experiment cannot establish that no conversion occurred.6
So what CAN we conclude? That pure fructose caused a remarkably small immediate blood glucose response in my particular experiment, compared with what I would expect from an equivalent amount of glucose.
That’s interesting by itself! But we would need a longer experiment, and ideally isotopic tracers, to determine where the fructose actually went.
Keep reading, because this distinction has some potentially important implications for people with type 1 diabetes, type 2 diabetes, and even healthy people…
Why does this matter?
For people with diabetes who are dosing insulin, this is potentially very important. Different carbohydrates can produce very different blood glucose responses, even when the total carbohydrate content is identical.
For example, fruits contain varying combinations of glucose, fructose, sucrose, starch, and fiber. The exact proportions vary considerably between different fruits. Although sucrose itself contains equal amounts of glucose and fructose, that doesn’t mean every fruit is 50% glucose and 50% fructose.
Let’s say I’m going to eat a small apple containing 14g of total carbohydrate. My insulin-to-carbohydrate ratio for this example is 1:77, which would ordinarily suggest 2 units of insulin.
But does that mean I actually need exactly 2 units for this apple?
Not necessarily! Some of the carbohydrate is fiber, and some is fructose, which generally produces a smaller immediate blood glucose response than glucose. However, because fructose MIGHT eventually be converted into glucose, I cannot simply subtract all the fructose and assume that it requires no insulin.
My experiment suggests that fructose may have a substantially different immediate insulin requirement than glucose, but it also does NOT establish that I should automatically cut my apple bolus in half. That would require additional experiments measuring the response to the actual food over a longer period.
Meanwhile, if I eat a slice of white bread containing 14g of total carbohydrate but only 1g of sugar, much of the remaining carbohydrate is starch. Digestive enzymes can convert that starch into glucose, potentially causing a substantial rise in blood glucose even though the bread doesn’t taste sweet.
The important takeaway is that two foods containing the same number of carbohydrate grams can produce very different glucose responses. An insulin-to-carbohydrate ratio is a useful starting point, but it doesn’t capture all the complexity of carbohydrate metabolism.
Hopefully you can see from this small example that an insulin-to-carbohydrate ratio alone cannot dictate exactly how much insulin you need for a particular food. In fact, there’s WAY more nuance than this, involving different types of carbohydrates that I didn’t discuss in detail (like allulose and maltose), as well as protein, fatty acids, exercise, and the timing of digestion and absorption. Different foods can produce different glucose profiles, even when their nutrition labels look similar. I hope to address some of these questions in a more advanced-level post in the future.
So is fructose a “free” sugar?
You may have postulated by now that if fructose doesn’t make the blood sugar meter move, it’s a “free sugar” – just like other non nutritive sweeteners like aspartame, stevia, and erythritol.
My answer to this is: probably not!
If you pay attention to nutritional news, you’ve probably heard warnings that fructose “turns into fat.” But the reality is a little more complicated.
Remember that my experiment only measured blood glucose. It didn’t measure fructose oxidation, glycogen storage, or fat production. So we cannot conclude that because my blood glucose didn’t rise, the fructose must have been converted into fat.
In fact, human isotope-tracer studies suggest that during the first few hours after ingestion, less than 1% of fructose is directly converted into circulating triglycerides, while much larger proportions are converted into glucose, lactate, or oxidized for energy.8
That doesn’t mean fructose can’t contribute to fat accumulation over longer periods. It can! But the dose, overall energy balance, and metabolic conditions matter.
Here’s what the research suggests:
- Fructose can be converted into glucose, lactate, glycogen, and fat, or oxidized for energy. The relative importance of these pathways depends on metabolic conditions.
- Exercise can increase the oxidation of ingested carbohydrates, including fructose, and alter how those carbohydrates are stored.9 However, that doesn’t mean fructose simply bypasses the liver and goes directly to working muscles.
- High fructose intake can stimulate hepatic de novo lipogenesis (the production of new fat by the liver). However, acute conversion into circulating triglycerides is relatively small, and changes in fat oxidation and clearance may also contribute to elevated triglycerides.
- Controlled feeding trials suggest that excess calories from sugar-sweetened beverages containing fructose can increase liver fat. However, replacing other energy sources with fructose-containing sugars without increasing total calories has generally not produced the same effect in these trials. This distinction is important when interpreting studies about fructose and fatty liver disease.10
Based on just that information alone, my personal decision has been to keep my fructose consumption relatively low, particularly when I’m sedentary. I generally limit myself to modest portions of fruit, such as a small apple or a bowl of strawberries or raspberries.
During long bike rides, I’ve often eaten larger portions of fruit because I’m burning substantial amounts of energy. Research suggests that exercise can increase fructose oxidation, so it’s plausible that my body handles fructose differently during a long ride than when I’m sitting at my desk.
However, this does NOT mean that working muscles necessarily consume fructose directly before it reaches the liver, or that exercise completely eliminates the potential metabolic effects of fructose.
I also want to correct something about blood fructose concentrations. The research I cited earlier reports peak plasma fructose concentrations of approximately 3-11mg/dL following relatively large fructose doses of 50-150g.11
That does NOT mean eating a small apple will produce a concentration of 11mg/dL. Fructose is absorbed, distributed, and metabolized continuously, so we cannot calculate its blood concentration simply from the amount eaten and a person’s body weight.
An ordinary glucometer cannot tell me how much fructose is circulating in my blood, so I don’t know what concentration I reached during my experiment.
Finally, it’s worth distinguishing fructose in whole fruit from large quantities of added sugars. Whole fruit contains fiber, water, and other nutrients, and the human evidence for metabolic harm from modest whole-fruit consumption is substantially weaker than the evidence concerning excess calories from sugar-sweetened beverages.
There is one more question about fructose that particularly interests me as someone with type 1 diabetes: Could it contribute to glycation in ways my glucose meter doesn’t capture?
Fructose and glycation
If you have diabetes, you’re probably very familiar with the HbA1c test. This measures the percentage of hemoglobin that has become glycated, primarily through exposure to glucose. Glycation is a non-enzymatic chemical reaction in which sugars react with proteins and other molecules. Over time, some of these reactions can lead to the formation of advanced glycation end products (AGEs).
AGEs are implicated in diabetic complications, although they are only one part of a much more complicated process involving oxidative stress, inflammation, vascular dysfunction, and other mechanisms.12
Why am I bringing this up?
Because I read something fascinating: Under certain experimental conditions, fructose can react with proteins approximately 8-10 times faster than glucose to form glycation products!
At first, this sounded alarming. If fructose is so much more reactive than glucose, could it be causing damage that my blood glucose meter and HbA1c test aren’t detecting?
Possibly! But there’s an important complication.
Although fructose is more chemically reactive than glucose in certain laboratory experiments, its concentration in human blood is normally much lower. The review discussing this phenomenon notes that circulating fructose concentrations are typically only about 1% of circulating glucose concentrations.13
This means we cannot simply multiply fructose’s chemical reactivity by the amount we eat and conclude that dietary fructose causes more glycation damage than glucose.
There is also a distinction between fructose produced inside tissues through metabolic pathways and fructose circulating in the blood after a meal. The biological consequences may be different.
So here’s where I land: Fructose-mediated glycation is an interesting and potentially important mechanism, but the evidence does not currently establish that eating modest amounts of fructose, particularly from whole fruit, produces greater diabetic complications through this pathway.
For now, I consider it a hypothesis worth investigating rather than a proven reason to avoid fructose entirely.
My original experiment taught me something interesting about the immediate blood glucose response to fructose. But it didn’t tell me what happened to the fructose afterward, or whether those metabolic pathways are beneficial or harmful over the long term.
There’s clearly a lot more to learn!
P.S.
I started writing this post Oct 15, 2019 and finally got to publishing it in August 2023! I’ve got a lot more for you, but it takes a long time to do my research…
References & Footnotes
- Reference: Starch digestion and absorption in nonruminants, G. M. Gray, 1992, https://pubmed.ncbi.nlm.nih.gov/1729468/
- Reference: Molecular disassembly of starch granules during gelatinization and its effect on starch digestibility: a review, Shujun Wang and Les Copeland, 2013, https://pubmed.ncbi.nlm.nih.gov/24096569/
- Reference: Short-chain fatty acids and human colonic function: roles of resistant starch and nonstarch polysaccharides, David L. Topping and Peter M. Clifton, 2001, https://pubmed.ncbi.nlm.nih.gov/11427691/
- Reference: Fructose metabolism in humans – what isotopic tracer studies tell us, Sam Z Sun, 2012, https://www.ncbi.nlm.nih.gov/pmc/articles/PMC3533803/
- Reference: Biochemistry, Fructose Metabolism, Sagar J. Dholariya et al, 2018, https://www.ncbi.nlm.nih.gov/books/NBK576428/
- Reference: Fructose metabolism in humans – what isotopic tracer studies tell us, Sam Z. Sun and Mark W. Empie, 2012, https://pubmed.ncbi.nlm.nih.gov/23031075/
- Note: An insulin-to-carbohydrate ratio (I:C) is a personal estimate of how much insulin is needed for a given amount of carbohydrate. It can vary significantly between individuals and within the same individual depending on exercise, time of day, and other factors. My ratio in this example reflects the period when I performed the experiment, not necessarily my current ratio.
- Reference: Fructose metabolism in humans – what isotopic tracer studies tell us, Sam Z. Sun and Mark W. Empie, 2012, https://pubmed.ncbi.nlm.nih.gov/23031075/
- Reference: Exercise performed immediately after fructose ingestion enhances fructose oxidation and suppresses fructose storage, Léonie Egli et al., 2015 (online publication), https://pubmed.ncbi.nlm.nih.gov/26702120/
- Reference: Important Food Sources of Fructose-Containing Sugars and Non-Alcoholic Fatty Liver Disease: A Systematic Review and Meta-Analysis of Controlled Trials, Danielle Lee et al., 2022, https://pubmed.ncbi.nlm.nih.gov/35889803/
- Reference: Fructose metabolism in humans – what isotopic tracer studies tell us, Sam Z. Sun and Mark W. Empie, 2012, https://pubmed.ncbi.nlm.nih.gov/23031075/
- Reference: Advanced Glycation End Products and Diabetic Complications, Singh VP, Bali A, Singh N, Jaggi AS., 2014, https://www.ncbi.nlm.nih.gov/pmc/articles/PMC3951818/
- Reference: Formation of Fructose-Mediated Advanced Glycation End Products and Their Roles in Metabolic and Inflammatory Diseases, Alejandro Gugliucci, 2017, https://pubmed.ncbi.nlm.nih.gov/28096127/






















Thank you, Brian, for explaining much of the mystery so clearly.
Peter Attia’s podcast had a deep dive into fructose. Might be worth a listen if you have 2 hours. https://peterattiamd.com/rickjohnson2/
Brian – Glad to know that you listen to Peter Attia. I do to, and have listened to all of his episodes involving metabolism… even the stuff related to type 2 diabetes, which I do not have. Thanks for mentioning Peter; he is one of my favorite podcasters. So thorough.
Wow Brian! This is really interesting information. I knew the basic information regarding glucose/white sugar and fructose/fruit sugar and how the body converts various foods to glucose/sugar. I had no idea what a huge load on the liver fructose could have! Now that we are aging and don’t exercise to the extent we used to that’s pretty thought provoking!